Digistain Prognostic Score - Breast
Breast Cancer Recurrence-Risk Information
What is the Digistain Test?
Digistain is a quantitative histopathology platform using a validated multivariate statistical model. It is UKCA-marked in accordance with the UK Medical Devices Regulations 2002, registered with the MHRA, and designed to assess the risk of recurrence in breast cancer patients following surgery. It provides risk stratification information to support MDT discussion; not intended to replace clinical judgement.
The test generates a clear, easy-to-interpret risk stratification output. Digistain provides recurrence-risk information for consideration by the treating clinical team.
Digistain is for invasive breast cancer patients who are:
Stage I - II
HER2-
ER+
up to 3 positive lymph nodes
Why Digistain?
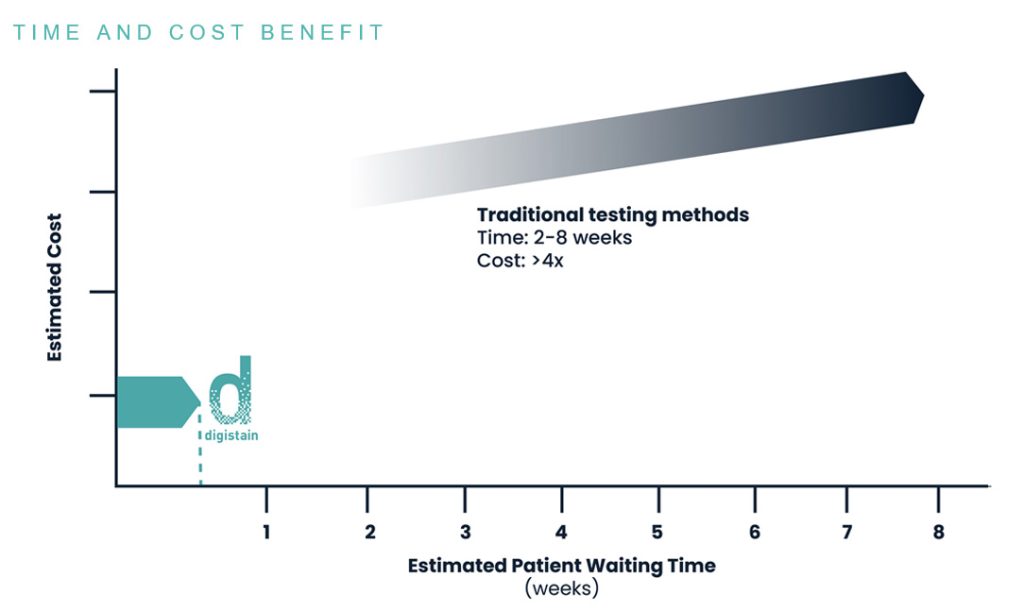
Digistain operates on routine FFPE tissue sections, requiring no molecular extraction and integrating seamlessly into existing histopathology workflows — designed to fit existing histopathology workflows, as a significantly lower-cost alternative to RNA-based genomic testing.
Key Benefits:
CLEAR insights on likelihood of breast cancer recurrence within the next 10 years
FAST results returned within 1-2 days of specimen receipt at our UK laboratory
LOWER COST designed as a significantly lower-cost alternative to RNA-based genomic testing
SEAMLESS integration with existing clinical workflows
Our Technology
Rapid Risk Stratification
Digistain was created by cancer researchers and physicists from Imperial College London to offer a faster, lower-cost approach to recurrence-risk information.
Our optical scan technology captures a unique spectral signature from each biopsy creating over 10,000 data points unique to the individual biology of a patient. We then use a validated multivariate statistical model to analyse the imaging data and calculate a Digistain Prognostic Score that provides recurrence-risk information.
Digistain Prognostic Score – Breast is an in vitro diagnostic test for professional use. The result is an estimate of the risk of recurrence and is probabilistic. It is used with, and does not replace, established clinico-pathological factors and clinical judgement. Treatment decisions remain with the treating clinician.